The Relief Mineral For Fibromyalgia
Ad Copy
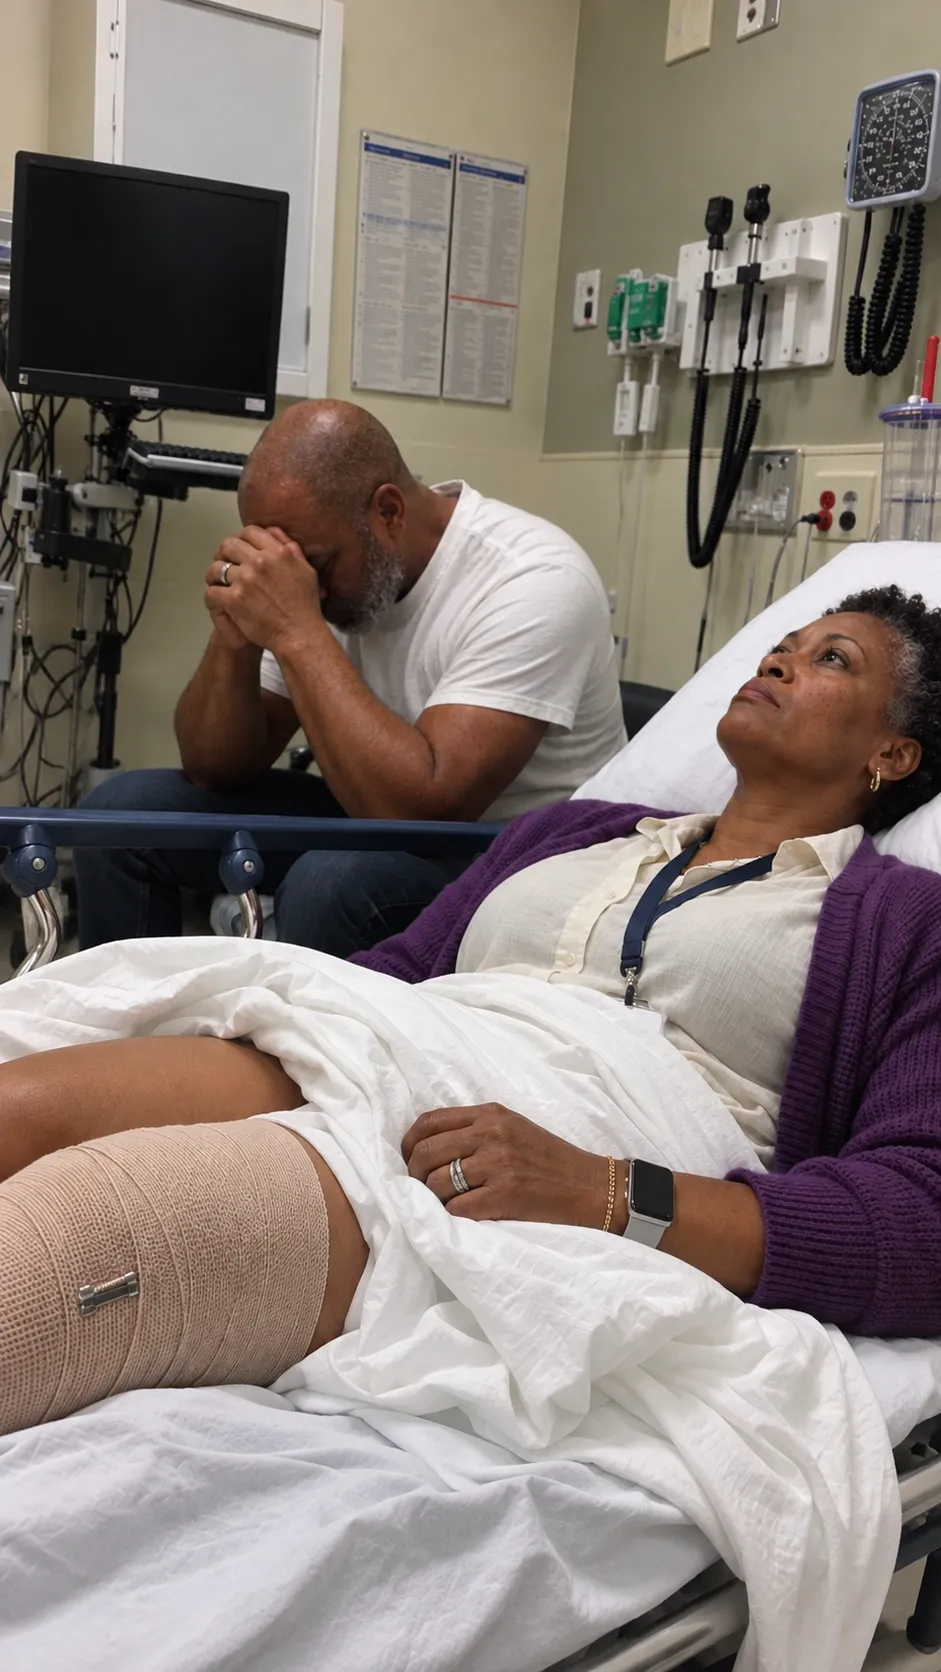
I have spent nineteen years in rheumatology doing one thing. I subspecialize in fibromyalgia and central pain disorders — the mechanics of why your nervous system becomes sealed in a state of permanent overdrive, why the pain extends into every region of your body, why migraines begin compounding on top of it, and why every prescription you try delivers less relief each cycle. And if you are peeling yourself off the mattress every morning convinced someone dragged your body through gravel overnight, your Cymbalta plateaued months ago, and the migraines are crashing down on top of the fibromyalgia like a second affliction your doctor never even brought up... I am about to lay out exactly what they have been missing. And why they are structurally incapable of finding it. And once you understand this, you are going to be livid. My name is Dr. Rebecca Yates. Board-certified rheumatologist. Nineteen years in practice. Subspecialty: fibromyalgia and central sensitization. Johns Hopkins fellowship. Over three thousand fibromyalgia patients seen. Published in The Journal of Rheumatology and Pain Medicine. And I am stepping outside my own profession's walls to put this in front of you. Because three facts have been sitting in plain sight, and no one has ever lined them up for you. First — your body has been broadcasting that something measurable has gone wrong inside it. Second — the medical establishment has been chalking it up to your emotional state, your bedtime habits, your supposed overreaction to discomfort. And third — a pharmaceutical industry exists that profits every single month you stay locked into a drug that is fading, and not a single product in that revenue stream was constructed to address what is actually pinning your nervous system in crisis mode — the fibromyalgia AND the migraines as one. So let me take you through what unfolded with one of my patients, because what happened to her is going to expose exactly how inverted this whole apparatus is. Her name is Joyce. Fifty-two years old. Manned the front desk at a nursing home in Memphis from the age of seventeen. For YEARS — seven unbroken years — she had been living inside this. The diffuse, everywhere aching that never subsides. Not arthritic swelling. Not a sports injury. The variety of pain that inhabits your entire body without settling in any one place — shoulders, hips, lower back, arms, jaw. A searing that shifts location. A pounding that compounds. A heaviness saturating her whole frame that twelve hours of rest cannot dissolve. And then the migraines appeared. Year three of the fibromyalgia. Six migraine days monthly heaped on top of the ceaseless body pain. A visual aura descending twenty minutes before the strike — the shimmering crescent hovering at the periphery of her sight, the blind spot unfurling outward. Then the unilateral, pulsing devastation. Light sensitivity so profound she would seal every shade and lower her forehead onto the cold kitchen floor. Nausea that held for the duration of every attack. A postdrome fog that clung for two full days afterward. Two distinct conditions. Running concurrently. One inadequately addressed. The other never addressed at all. She quit accepting invitations. Abandoned making plans she might need to cancel. Avoided walking anywhere near the recliner because lifting herself out of it would rob her of the next two hours — and on the severe days, the motion alone would ignite an aura. Her husband concluded she had quit fighting. But where Joyce grew up, you do not slow down for pain. You do not phone in absent. You do not permit another living soul to see it written on your face. She had not quit fighting. She had been pulling herself to that front desk five mornings a week for thirty-five years without a single absence. She was not quitting. She was splintering. And here is what makes my stomach turn. I was merely the second doctor who had ever sat across from her in her entire life. One physician before me. Her general practitioner. One exam room. One prescription pad. Across seven years. Nobody else ever brought in. He prescribed Cymbalta. An antidepressant. Before he conducted a single diagnostic workup. The relief held approximately three weeks. Then the pain reasserted itself harder. When the Cymbalta ceased delivering, he stacked on painkillers. Then cortisone injections on a quarterly rotation. Then muscle relaxants for the nighttime hours. She added weight and the pain remained everywhere. He communicated to her that chronic fibromyalgia was "something she would simply have to cope with." He was fixed on the chart when those words left his mouth. Not on her. With an assuredness in his voice that made me want to circle that desk and inquire at what precise moment he had ceased perceiving a person in that room. And the migraines? He never engaged with them. Not on a single occasion. Never dispatched her to a neurologist. Never associated them with the fibromyalgia. Never entered them into her record as a separate clinical issue. Seven years of migraines mounting on top of fibromyalgia and the woman positioned across from him was bearing both alone because nobody considered asking. And you know what he communicated each time her laboratory work returned? "Your numbers look normal." "This is fibromyalgia. Likely stress-driven." "The migraines are most probably tension-type headaches." "Focus on managing your stress." ABSORB THAT. This woman was observing her life collapse under pain that never released its grip and migraines that kept accumulating on top, and she was not even receiving two independent treatment pathways — she was receiving a single unfinished pathway from a man who had stopped perceiving her years prior while the migraines went wholly unrecognized. Sandra — a separate patient of mine, the one I have documented before — had been rotated through four distinct specialists. Joyce had been forsaken by one. But here is where it turns worse still. And this is the element that will not leave me. The Cymbalta that had initially supplied three weeks of partial reprieve was now providing ten days. The painkillers were ceding ground. The muscle relaxants were scarcely carrying her through until morning. And the migraine frequency was ascending — from four days monthly to six, then to eight. No intervention. No specialist consultation. No protocol. She expressed to me: "It is as though my entire nervous system has resolved to do this irrespective of what I put in my body. The fibromyalgia intensifies and the migraines intensify at the identical rate. And not one person has ever presented the migraines to me as a distinct condition. I believed they were simply an extension of the fibromyalgia." I watched this woman — who had labored through the pain for thirty-five years without protest, who had never missed a single day, who had sustained both conditions without one referral — grow worse. Not level off. The ceiling continued descending. Across both conditions in unison. And for an extended period, I had no explanation. Until I was seated opposite a sixty-eight-year-old NMDA receptor investigator at a conference in Vienna. And across ninety minutes he conveyed more about why fibromyalgia and migraines jointly resist treatment than I had assimilated in nineteen years of rheumatology practice. October 2024. Vienna. The European Pain Federation Congress — the premier pain science conference on the European continent. I was present because a colleague had pressed me to attend a lecture on NMDA receptor disruption in central sensitization and its intersection with migraine comorbidity. I was standing on my own during a coffee interval, working to push my own body out of my thoughts. At fifty-one, my personal symptom pattern had been compounding for sixteen months. Shoulders seized by noon. Hips that fought me each time I lifted myself from my desk chair. A weariness that caffeine could not breach. And across the last six months, migraines had started landing — four each month and rising. I identified the pattern from my own clinical population reflected inside my body. The fibromyalgia presentation emerging first, the migraines layering in afterward. And nothing I had been counseling patients on for nineteen years was altering either condition in me. That is when I spotted him. Dr. Klaus Lindner. Sixty-eight years old. Retired MD-PhD out of the University of Zurich. Thirty-five years dedicated to studying NMDA receptor mechanics in chronic pain states and in particular the role of mineral cofactors in receptor gating — encompassing both fibromyalgia and migraine biology. I had cited one of his papers in my fellowship work. I never anticipated seeing him there. He was positioned beside the coffee table looking as grounded as a man two decades younger, wholly unbothered. I walked up to him. Offered my name. And because I had spent the full morning battling what my own body was signaling, I said something I would never have confessed to any colleague inside my own hospital walls. "Dr. Lindner — could I ask you something. Speaking as a patient." He studied me a beat longer than customary. Then he asked what it was. I laid it out. Nineteen years of rheumatology. My own body starting to echo what I observed in my patients — the fibromyalgia pain installing itself first, then the migraines settling on top. Nothing my profession was equipped to offer had interrupted the advance of either one. He did not give a courteous smile. He did not launch into an explanation. He set his cup aside. He said: "It is the gate. And it is the very same gate for both." I registered those words and my reasoning locked. Because this was a connection I had never, across nineteen years, heard expressed in this manner — fibromyalgia and migraines originating from a shared upstream driver. He said: "Come with me." He grabbed a napkin from the coffee station and rendered two diagrams alongside each other — an NMDA receptor in its sealed state and the identical receptor forced permanently open with a dark cloud labeled "central sensitization" and an arrow ascending to a second label: "cortical spreading depression." He said: "Same receptor. Same deficiency. Two conditions. Can you tell me why your fibromyalgia patients keep developing migraines?" I could not. Not in these terms. He said: "The NMDA receptor is a gate inside your nervous system that presides over two operations simultaneously. First — it dictates whether pain signals are transmitted or suppressed. In fibromyalgia, that gate becomes forced permanently open. Every ordinary signal — pressure, heat, the faintest brush — is magnified into pain. That is central sensitization. Second — that identical receptor modulates cortical excitability within the brain. When the gate is stuck in its open position, the threshold for cortical spreading depression falls apart. That is the electrical surge that rolls across the brain surface and ignites a migraine episode. The aura is that surge. The pain that ensues is the trigeminal nerve firing it provokes." He touched the drawing. "One receptor. One deficiency. Two conditions that every medical facility handles as disconnected issues with disconnected treatment plans. The question every rheumatologist and every neurologist should be raising — and nearly none of them do — is: why does the gate remain stuck?" He proceeded. "The gate stays open because the biological key your body depends on to close it has been depleted. That key is magnesium — specifically, intracellular magnesium. The magnesium housed within your cells. Not the magnesium floating through your blood. When cells have been emptied of magnesium, the NMDA receptor cannot return to its closed position. Pain signals stream through without filter — that is the fibromyalgia. And the cortical excitability threshold deteriorates — that is the migraines. Both conditions degrade at an identical pace because both are sustained by the same cellular emptiness." I felt something I had not experienced in a long while inside a professional environment. The distinct nausea that arrives when you comprehend you have been treating a symptom while the source ran unchecked. He proceeded. "You have been managing the sensitized nervous system for years. The Cymbalta softens the fibromyalgia pain signal at the output end. The painkillers bury it. The muscle relaxants sedate it. But none of those close the gate at the origin. And the migraines? If no one even directed her to a neurologist, then the second condition saw no management whatsoever. The gate holds open because the cells are devoid of the magnesium to seal it. The fibromyalgia approach handles the pain at the endpoint. The migraine approach was never constructed. The deficiency feeding both goes unimpeded." "And the reason each prescription window compresses over time — for both conditions — is that the depletion is worsening. Cortisol — the stress hormone fibromyalgia patients overproduce, because the unrelenting pain itself manufactures cortisol — eats through magnesium reserves each night you sleep. The cells empty further. The gate expands. The pain sharpens. The migraine threshold erodes. At a certain point the prescriptions are trailing a progressively more sensitized system across both fronts, and no dose recalibration can compensate for what is absent at the cellular level." I sank onto the edge of the coffee table. He pressed on. "And here is the reason no laboratory panel ever flagged it. Standard bloodwork measures serum magnesium — the magnesium distributed in the bloodstream. That accounts for one percent of the body's total magnesium. The other ninety-nine percent is lodged inside the cells, where the real deficit resides. Your patient's results show normal every instance. The doctor notes a satisfactory figure. Issues another prescription for the fibromyalgia. Never pursues a neurological evaluation for the migraines. The cellular deficit marches on. The gate persists. Both conditions advance." And then he stated the part that landed on me like concrete. "And for women whose physiology is constructed like your patient's, the reference value that is supposed to indicate a deficiency on that blood panel is calibrated against a lower baseline. So a 'normal' result on that laboratory form was never calibrated with her biological reality as the reference. He ran the wrong panel. Read the wrong figure. Applied the wrong baseline. And assured her nothing was the matter. For seven years." Then he uttered the sentence I replay when sleep will not come. "You cannot seal the NMDA gate by treating the pain signal at the output while the cells remain emptied of the mineral they need to seal it. You have to place magnesium inside the cell first. And the moment you do, both conditions respond — because they were always a single upstream problem." That is the answer. That is the complete answer. That is the sentence that clarifies why the Cymbalta keeps shortening its window AND the migraines keep escalating at the same pace. And here is the part that made my blood pressure spike. We possess this knowledge. A fraction of us. The investigators who research NMDA receptor physiology. The scientists who generate evidence proving that intracellular magnesium depletion causally initiates central sensitization and cortical hyperexcitability — not merely accompanies them. The papers in The Journal of Pain Research. The meta-analyses establishing that magnesium deficiency sustains chronic NMDA receptor overactivation across both fibromyalgia and migraine populations. It sits in the published literature. Peer-reviewed. Accessible to anyone with a search engine. But it will never enter the training of a working rheumatologist. It will never emerge in a fibromyalgia appointment. It will never be connected to the migraines during a neurology session — if you ever get the fortune of being referred to one. It will never be printed on the handout in your doctor's office. Why? Because nobody can patent magnesium. There is no billing code for restoring intracellular mineral levels. There IS a billing code for a Cymbalta prescription, and a painkiller refill, and a cortisone injection, and the bloodwork you complete every six months, and every scheduled visit for the balance of your life — from one doctor who never lifts his eyes from the chart. Joyce had surrendered seven years. Not nineteen thousand dollars like Sandra. Joyce lacked access to four specialists to accumulate bills across. She had a single room, a single physician, a single prescription pad. But the price was not counted in currency. It was counted in years of her life that vanished and will not return. It was counted in shifts she powered through while tears ran down her face in the nursing home restroom. It was counted in the recliner she descended into each evening because her body could not sustain her in any other position. There is profit in a patient whose pain keeps amplifying and whose migraines keep multiplying. There is none in a patient who finally corrects the root of both. So I traveled home from Vienna, and I did what a rheumatologist truly does when she has just been shown that her entire model is upside down. I read every citation Klaus had referenced. I read every citation those citations had listed. I returned to papers I had skimmed through a decade earlier and understood their implications in an entirely new way. And what I kept arriving at was the form of magnesium. Not the magnesium from the pharmacy aisle. Not the capsule Joyce had already sampled and discarded because it produced nothing — for the fibromyalgia or the migraines. That was magnesium oxide. Now, I am not going to sit here and claim that magnesium is without effect. It has one. But the version sitting on the retail shelf is the wrong version. And nobody has broken down the reason for you. Magnesium oxide is what every doctor defaults to because it is affordable and ubiquitous. But the vast bulk of it passes unabsorbed through your digestive system without ever breaching a cell membrane. It never makes contact with the cells where the deficit actually persists. An independent assessment evaluated absorption metrics across all available magnesium forms. Oxide registered the lowest cellular bioavailability among every option tested. The formulation that reliably penetrated intracellular targets was coupled with glycine — an amino acid that serves as a molecular carrier through the intestinal wall. You could ingest magnesium oxide each night for a full year and your cells would remain depleted. The fibromyalgia would endure. The migraines would continue accumulating. If you ever gave magnesium a chance for fibromyalgia or migraines and registered no improvement, it was not the mineral that came up short. It was the delivery vehicle. You did not fail magnesium. The formulation never carried it to the destination where it was needed. And when Joyce informed me she had given it a try, something broke open in my chest. Because I already recognized what she was about to disclose. She told me she had taken that identical bottle to her Mama. The oxide bottle. She lifted it from the shelf at the grocery store and delivered it to the recliner where her Mama inhabited the closing years of her life, trusting with every fiber she was extending relief. The front of the label stated Magnesium. The rear stated oxide. She had been supplying her Mama four percent of what her cells actually demanded and telling herself each evening it was accomplishing something. Her Mama had worked the cafeteria counter until the pain inhabiting her own body hauled her off her feet. Where Joyce grew up, you do not bow to pain. You do not remain in bed. You do not let a single individual on earth observe it in your face. Her Mama lived by that principle until the recliner became the only location her body permitted her to occupy. She passed in 2019. In that same recliner. And Joyce was headed down the identical path. And then there is the second mechanism. Even if you manage to deliver magnesium to the cell accurately — even if it arrives at the NMDA receptor and initiates gate closure — there is a force that keeps pulling it back out every single night. Cortisol. The stress hormone. Fibromyalgia patients generate it in abundance — the persistent pain itself stimulates cortisol output, which burns through magnesium stores during sleep. You seal the gate throughout the day and cortisol drains the magnesium by nighttime. The gate swings open again by sunrise. The pain reappears. The migraine threshold sinks once more. The loop sustains itself. You need something that shatters the loop from both ends at once. Ferries magnesium into the cell AND suppresses the cortisol signal that evacuates it overnight. That is exactly what magnesium bisglycinate delivers. It is coupled with two molecules of glycine — an amino acid that simultaneously functions as a calming neurotransmitter. The glycine executes two operations at once that no clinical setting, no prescription medication, and no alternative magnesium formulation has ever managed in tandem. First: the glycine carries magnesium directly across the intestinal membrane and into the cell. Past the digestive tract. Past the bloodstream. Straight into the cells where the NMDA gate is lodged open. Second: the glycine itself engages the pathways that maintain cortisol at elevated levels overnight. It dampens the cortisol signal. The overnight extraction ceases. The magnesium persists inside the cells long enough to truly shut the gate. The loop ruptures from both ends in one movement. The gate shuts. The pain signals stop streaming through. The cortical excitability threshold recovers. Both conditions respond — because both were always generated by the identical deficit. That is the foundational reason it produces results where every other option does not. So I revisited the research with a singular question in mind. What is the version of this that genuinely delivers magnesium bisglycinate at 400mg — the dosage the evidence base supports for NMDA receptor restoration — with zero oxide content, third-party verified for purity, and produced under GMP certification, in a form I would hand to my own patient? There was one. Not a capsule from a drugstore shelf. Not a powder you stir into liquid. A gummy — two gummies before sleep, formulated purely around magnesium bisglycinate with no competing compounds affecting absorption. It was called Celuvida. I tested it on myself first, before I offered it to a single patient. Two gummies before sleep. Every night. Week zero: the widespread aching I had been living with for sixteen months. Shoulders rigid by noon. Hips that punished me each time I stood from my office chair. A fatigue that no stimulant could penetrate. And four migraines that month — the visual aura materializing on cue, the postdrome knocking me flat for a day and a half after each occurrence. Week one: nothing striking. A single morning where the rigidity I carried into my opening three consultations was reduced. I logged it. Attributed it to chance. Week three: the moment I still cannot adequately convey. I was standing at my kitchen counter putting away dishes from the dishwasher, coffee in one hand. I had gotten off the couch five minutes earlier. I had not made the sound. I placed the mug on the counter and stood there searching my memory for the last time I had risen from any surface without bracing for it. I drew a blank. And then a second awareness struck. I had driven to the office that morning along the highway segment where the sunlight at a particular angle had been sparking visual disturbances for months. I had driven the entire segment. No aura. No flinching. Week six: the morning rigidity had mostly evaporated. The aching across my shoulders that had been mounting to a peak by noon was muted. Not eliminated. Muted. And one migraine that month. Down from four. The postdrome resolved within half a day instead of stretching to two. Week ten: I withdrew from the follow-up appointment I had booked with a colleague for the fibromyalgia. And I withdrew from my next Botox appointment. Not because I had reached a conclusion. Because I had completed eight straight days without the widespread aching AND twelve straight days without a migraine — and I wanted to establish what my unassisted baseline genuinely was. The cells had not been replenished across nineteen years of clinical work. They had been running in deficit. And that deficit had at last been reversed. Both conditions moved at the same time — because they had always constituted a single upstream problem. Then I reached for the phone and called Joyce. I described what I had put my own body through. I relayed what Klaus had conveyed to me beside the coffee station. I told her that every prescription and every injection her prior doctor had provided — aimed exclusively at the fibromyalgia, while the migraines received absolutely no attention — had been targeting the pain signals while the cellular depletion holding the NMDA gate open continued operating beneath both conditions at once. And I said to her: "I want to attempt one thing before we explore anything else." Two gummies before sleep. Every night. She commenced that same week. Week two: her initial flare materialized. She informed me it registered as a level five instead of the level nine she had been experiencing. She labeled it "bearable without reaching for the heating pad." And the migraine she expected on day eleven — the one that had been arriving with clockwork precision — never appeared. Week four: she telephoned me from the nursing home. We both broke down, an hour apart. She had traversed the full length of the corridor and back to deliver a plate to a resident and come through the front desk doorway without paying for it the remainder of the day. No flare. No migraine set off by the fluorescent ceiling lights. The first instance in over three years. Week eight: the widespread aching that had been her constant shadow was muted. She captured it as "someone finally dialing down the noise." Not silenced. But dialed down. Dialed down enough that she could register the rest of her life again. And two migraine days that month. Down from eight. The episodes that surfaced were shorter in duration. The postdromes had cleared by evening. Week twelve: she committed to Sunday dinner. Pledged herself to a weekend trip with the women from her church. Stood in line at the grocery store with bags in her arms — an act that would have exacted two hours in the recliner six months prior. And sat through an entire church service under lighting she would have exited within forty minutes when the migraines were at their worst. The cost of what had failed her across seven years — the Cymbalta, the painkillers, the cortisone, the muscle relaxants, the copays from a lone doctor who never once shifted his gaze from the chart: seven years of her existence. The cost of what succeeded: two gummies before sleep. She arrived at that dinner in her real life. Not the contingency edition — the one constructed around heating pads and exit strategies and scanning every venue for the lighting that could trigger an aura. Actual plans. Actual commitments. The flare was no longer authoring her week. The migraines were no longer deleting her Sundays. She brought a plate to the table. Not out of obligation. Because her body permitted it. She won her life back. Now I am not going to manufacture urgency for you. But I will tell you what I have concluded as a fibromyalgia specialist who has witnessed both conditions merge inside the same patients for nineteen years. The NMDA gate does not reset on its own. Without intervention, the deficit deepens. The gate expands further. The cortisol continues incinerating whatever magnesium survives. The Cymbalta window compresses further. The migraines need no Botox recalibration because nobody addressed them at any point. The pain threshold keeps eroding and the migraine threshold keeps deteriorating — in parallel — because they were always anchored in the identical deficit. A nervous system that has existed in chronic sensitization for years does not reverse itself through inaction. Every month the cells persist in their depleted state is another month the gate holds open. That is the sole clock that governs this. So let me voice the thing nobody voiced to me for nineteen years. Aimed squarely at you. If a rheumatologist who subspecializes in the science of why fibromyalgia becomes treatment-resistant could pass sixteen months oblivious to this — sixteen months watching her own body unravel, watching her own migraines begin mounting, while she treated women carrying both conditions — then you have not come up short here. It is not your emotional state. It is not your sleep discipline. It is not your sensitivity to pain. It is not your triggers. The NMDA gate inside your nervous system has been jammed open because your cells have been drained of the one mineral they require to shut it — and nothing within the standard fibromyalgia protocol or the standard migraine protocol was conceived to deliver that mineral where it genuinely must go. Because nobody connected both conditions to the identical upstream deficit. And in certain instances, nobody even conceded the second condition was present. Celuvida includes free shipping and a 90-day money-back guarantee. Two gummies before sleep. Every night. If the aching has not moved, if the migraines have not diminished, if the Cymbalta window has not grown — complete refund. Every dollar back. No questions raised. And honestly? Even if you harbor doubts — especially if you harbor doubts, because so did I — give it a month. Allow your own body to render the judgment. Because nobody is going to hand this to you in a rheumatology practice or a headache specialty clinic. There is no billing code for it. There is no pharmaceutical representative who flies in to instruct on it. There is a sixty-eight-year-old NMDA researcher in Zurich who has been quietly asserting this for twenty years to anyone prepared to sit down and hear it. It is past time somebody brought it to you. celuvida.com/pages/woman-advertorial-fibromyalgia P.S. — I still prescribe Cymbalta. But strictly as support for a nervous system whose NMDA gate has been corrected. That prescription dampening pain signals while the gate persists wide open is what causes every treatment window to keep narrowing — for both conditions simultaneously. P.P.S. — If you stand at month sixteen the way I did — waking rigid every morning, the migraines descending on top of the fibromyalgia pain, the prescriptions starting to plateau — the depletion has been compounding the entire duration you have been adjusting your protocol. It does not wait for you to be ready. P.P.P.S. — Joyce asked that I add this. She told me her daughter Keisha is a nurse. Works the ward floor. And Keisha told her something that neither mother nor daughter has managed to stop thinking about. "Mama, I see women who look like you come through the ward every single week. Same pain. Same labs that come back normal. Same prescriptions that stop delivering. If I had known about the gate, I could have helped Grandma." She could not get to the end of that sentence. Grandma would have loved this. celuvida.com/pages/woman-advertorial-fibromyalgia 90-day money-back guarantee.
More from Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips

The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips

The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips
The Relief Mineral For Fibromyalgia
Black Women’s Health Tips

“Mom won’t get up.”
Black Women’s Health Tips

“Mom won’t get up.”
Black Women’s Health Tips

 Add to Chrome